Properties (16)
- purpleRed
- (Guetta et al., 2024)
•
Misophonia is related to stress but not directly with traumatic stress
Status:: #status/reviewed
Metadata
- Item Type: #journalArticle
- Authors:: Rachel E. Guetta, Marta Siepsiak, Yanyan Shan, Emily Frazer-Abel, M. Zachary Rosenthal,
- Date:
- Date Added: 1769056893000
- URL: https://dx.plos.org/10.1371/journal.pone.0296218
- DOI: 10.1371/journal.pone.0296218
- Cite Key: guettaMisophoniaRelatedStress2024
- Topics: [object Object]
- Tags:: #Misophonia,
- PDF Attachments
| Background/Purpose | Background- • Misophonia co-occurs with psychiatric disorders, but no disorder uniquely associated. • Prior studies show low current PTSD prevalence in misophonia using structured interviews. • Stress mechanisms implicated in sound over-responsivity in animal and human studies. • Perceived stress is transdiagnostic and linked to health outcomes. • No studies have examined perceived stress in relation to misophonia. • Unclear whether trauma history, PTSD diagnosis, PTSD symptoms, or perceived stress relate to misophonia severity. Purpose- • goal of assessing the relationships among Misophonia , stress, and traumatic stress. (page 11) • Examine relationships among misophonia, perceived stress, traumatic life events, PTSD diagnosis, and PTSD symptoms. • Determine whether perceived stress or traumatic stress better predicts misophonia severity. • Explore which PTSD symptom clusters contribute to misophonia severity. • Account for COVID-related stress. |
| Participants/samples | • N = 143 U.S. adults with self-identified auditory sound sensitivity. • Mean age ≈ 36.9 years. • ~70% female. • Exclusion: current psychosis, mania, anorexia nervosa. • Structured diagnostic interviews (SCID-5). |
| Measures | • Misophonia Questionnaire (MQ). • Duke Misophonia Questionnaire (DMQ) – symptom severity, impairment, coping. • SCID-5 – current and lifetime trauma-related diagnoses. • Life Events Checklist (LEC-5) – lifetime traumatic events. • Posttraumatic Stress Disorder Checklist (PCL-5) – PTSD symptoms and clusters. • Perceived Stress Scale (PSS). • Acute Stress Disorder Scale – Adapted for COVID (ASDS-C). |
| Procedures | • Online screening via REDCap. • Phone screening using MINI. • In-person or virtual structured SCID-5 interview. • Self-report questionnaires completed independently. • Composite DMQ severity score created from standardized symptom and impairment scores. • Multiple linear regressions controlling for age and sex. • Network analysis using EBICglasso regularization. |
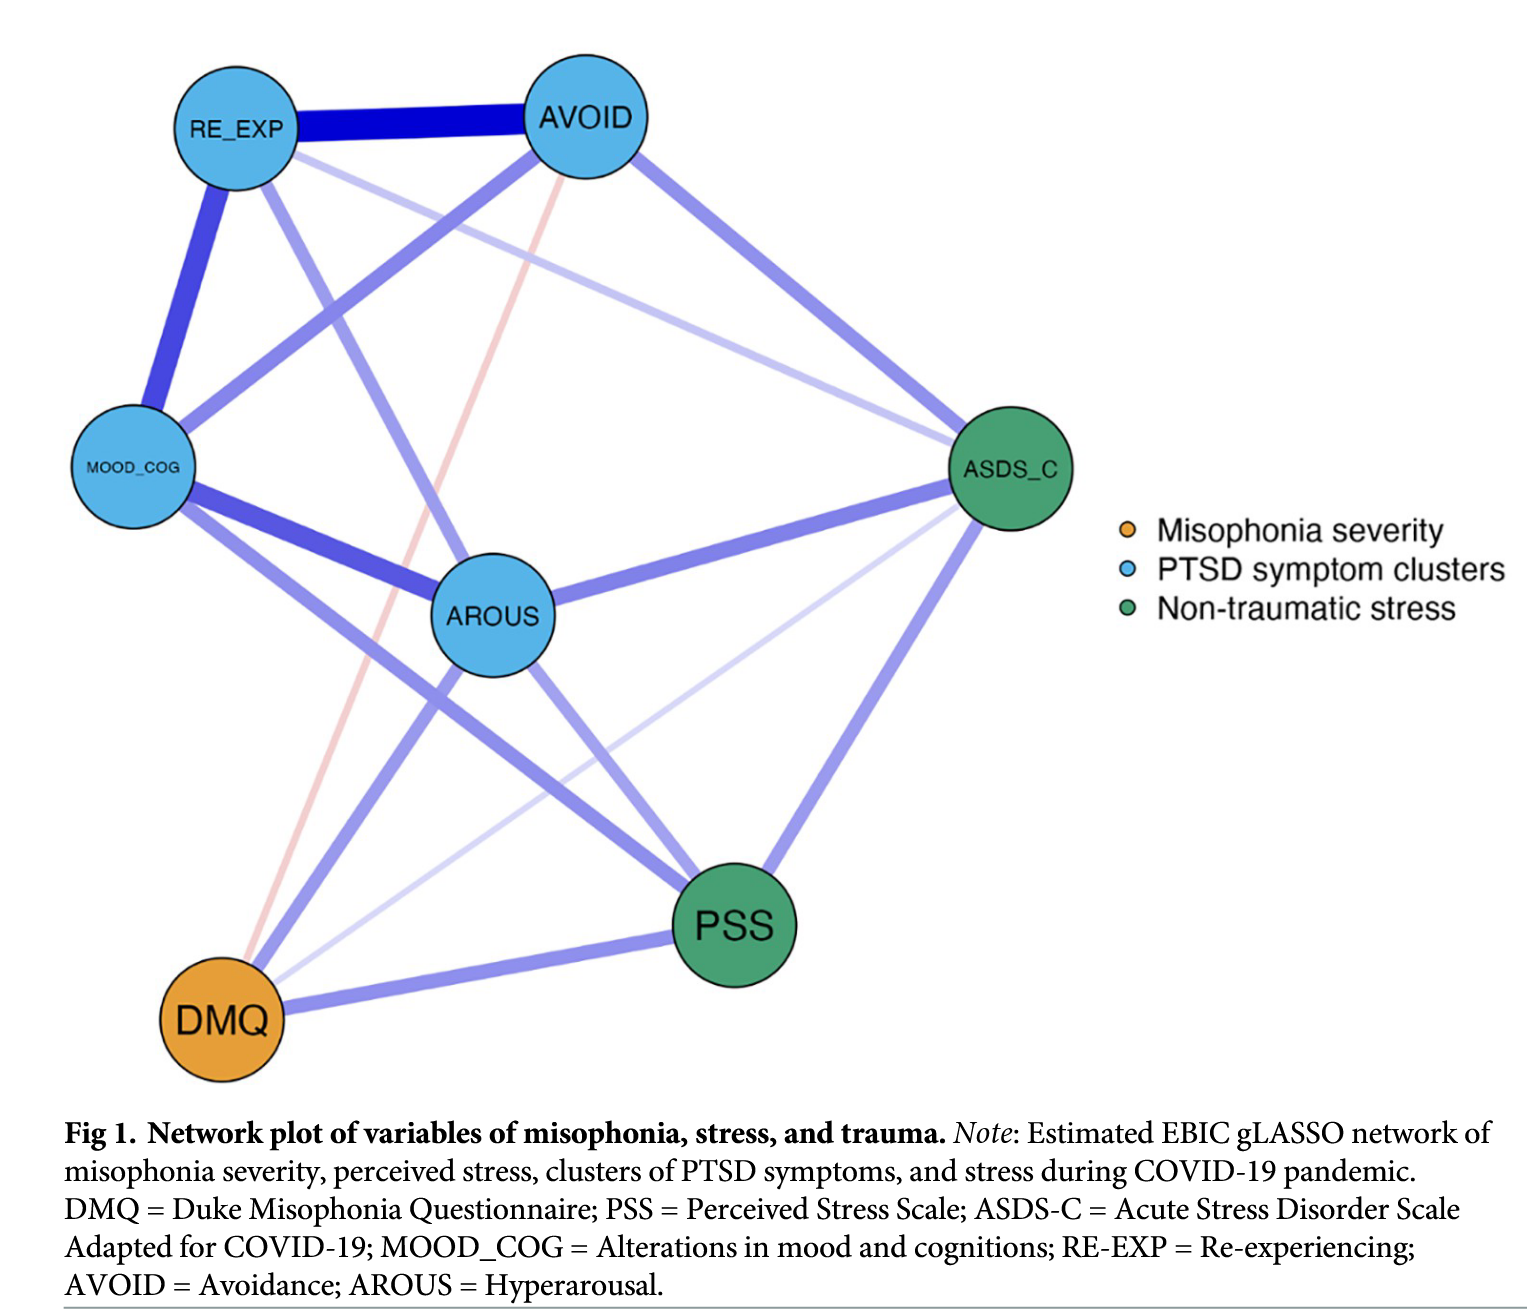
| Results | • Prevalence and trauma exposure • Current PTSD prevalence low; lifetime PTSD higher than general population estimates. • Lifetime trauma-related disorders present in subset. • Frequency of lifetime traumatic events not associated with misophonia severity. • Current or lifetime trauma-related diagnoses did not predict misophonia severity. • Bivariate associations • Misophonia severity positively correlated with perceived stress. • Misophonia severity positively correlated with total PTSD symptoms. • Hyperarousal showed strongest association among PTSD clusters. • COVID-related stress positively correlated with misophonia severity. • Multivariate models • Perceived stress significantly predicted misophonia severity over and above PTSD symptoms and COVID-related stress. • Perceived stress remained significant after controlling for number of lifetime traumatic events. • PTSD total symptoms did not predict misophonia severity when perceived stress included. • Among PTSD clusters, only hyperarousal predicted misophonia severity. • Age and sex not significant predictors. • Other PTSD clusters not significant. • Network analysis • Perceived stress and hyperarousal directly associated with misophonia severity. • Avoidance weak and negative association. • COVID-related stress weak association. |
| Discussion/Limits | Conclusion- • no evidence that PTSD is a causal factor in misophonia (page 13) • Hyperarousal, a trauma-related process not limited to Criterion A events, may be a key transdiagnostic treatment target in misophonia. This study identified hyperarousal as uniquely associated with misophonia severity. Treatment should involve idiographic assessment and process-based interventions aimed at reducing hyperarousal, prioritizing strategies the patient is willing and able to implement. Reducing hyperarousal may also downstream affect related processes such as anger, avoidance, anticipatory anxiety, and aversive cognitions. (page 14) • The authors conclude misophonia is not uniquely or causally associated with PTSD. • The findings indicate perceived stress, rather than traumatic stress, accounts for misophonia severity. • The data support hyperarousal as a transdiagnostic mechanism relevant to misophonia. • The authors conclude trauma history alone does not explain misophonia severity. • The findings indicate overlap in transdiagnostic stress processes between misophonia and trauma-related conditions. • The data support targeting perceived stress and hyperarousal in assessment and treatment. • |
| Limitations:: | • Sample not demographically representative. • Cross-sectional design; no causal inference. • No control for temporality of trauma relative to misophonia onset. • Reliance on self-report for PTSD symptoms (PCL-5). • ASDS-C not psychometrically validated. • Limited multimethod stress assessment. |
| Future Directions:: | • Longitudinal and prospective designs. • Examine childhood adversity and developmental timing. • Incorporate clinician-rated PTSD measures. • Use behavioral and psychophysiological stress measures. • Examine dispositional and transdiagnostic factors (e.g., neuroticism, emotion regulation). • Test transdiagnostic stress-reduction interventions in misophonia. |
| Statistics:: | • Current PTSD 3.5%; Lifetime PTSD 21.7%; Any current trauma disorder 11.9%; Any lifetime trauma disorder 32.9%. • Transportation accident 51.7%; unwanted sexual experience 36.4%; natural disaster 32.2%; other stressful event 30.1%; sudden unexpected death 29.4%. • LEC frequency × DMQ symptoms r = .02 (p = .799); × impairment r = .09 (p = .325); × severity r = .06 (p = .499). • DMQ severity × PCL-5 total r = .266 (p < .001); × hyperarousal r = .342 (p < .001); × PSS r = .374 (p < .001); × ASDS-C r = .264 (p < .001). • Regression (age, sex, PCL-5, ASDS-C, PSS): R² = .15; ΔR² = .13; PSS β = .30 (p = .004); others NS. • Regression adding LEC-5: R² = .15; ΔR² = .12; PSS β = .30 (p = .004); others NS. • PTSD diagnosis model: F(4,138) = 1.57 (p = .186); NS. • PTSD cluster model: R² = .19; ΔR² = .04; hyperarousal β = .27 (p = .022); re-experiencing, avoidance, negative alterations NS. |
| Relevance:: | • a paper Zack is on • a good source for background info on Misophonia comorbidities, and the role of stress in sound sensitivities in general |
Notes
key terms and concepts:
-
Misophonia – a sound intolerance disorder marked by strong aversion and heightened multimodal (physiological, cognitive, behavioral) emotional reactivity to certain repetitive auditory stimuli.
-
Perceived stress – the degree to which individuals appraise their lives and everyday situations as unpredictable, uncontrollable, or overloading.
-
Traumatic stress – symptoms associated with exposure to Criterion A traumatic events, including re-experiencing, avoidance, negative alterations in mood and cognition, and hyperarousal.
-
Hyperarousal – PTSD symptom cluster characterized by hypervigilance and startle reactions.
-
Life Events Checklist (LEC-5) – self-report measure of exposure to potentially traumatic events.
-
Duke Misophonia Questionnaire (DMQ) – multidimensional self-report measure assessing trigger frequency, affective, physiological, cognitive responses, coping, and impairment.
my engagement notes
my questions
my comments
Bookmarks
reading notes
zettelkasten
anxiety, features of OCD personality, and mood disorders as common Misophonia comorbidities
stress as an etiological factor for sound sensitivities
Guetta 2024 findings on perceived stress and traumatic events in Misophonia